Rural context, age-standardised cerebrovascular mortality, ageing and care networks in Japan
This edition separates the public explanation from the scientific record. No estimates were refitted and no new analyses or external validation were performed. The analytical periods, methods, limitations, figures and reported results below are retained from the existing article. The original publication date is 2026-10-19.
Design, estimands and statistical instruments
Statistical instruments
Descriptive comparisons of unweighted mean prefectural directly age-standardised mortality rates, with a common 2015 standard; medians across eligible medical areas; separately reported patient-flow distributions; independent recalculation of fourteen mortality contrasts. No spatially adjusted effect estimates, p-values or individual risk estimates are reported.
Territorial definitions
Rural context is the population share in non-urban MAFF 2017 municipal categories. The extreme rurality thirds contain 16 prefectures each, with 15 in the middle. SMA context cuts are medians (rural share 35.30%; population aged 75+ share 17.08%). Zero cardiologist counts are excluded from the finite ratio median and reported separately.
Denominators and compatibility
All-age age-standardised mortality is not mortality in people aged 75+. The 25.0% outflow figure is a median of territorial percentages, not a national patient proportion. The 2023 flow distribution is not joined to a local 2020 mortality/capacity ranking on the assumption of unchanged geography.
An ageing country needs care networks that reach beyond the city.
Japan’s cardiovascular challenge is also a question of place. Rural communities are ageing, specialist resources are unevenly distributed, and some patients receive hospital care outside their own medical area. Bringing these dimensions together helps identify where a stronger local-to-regional care network deserves attention.
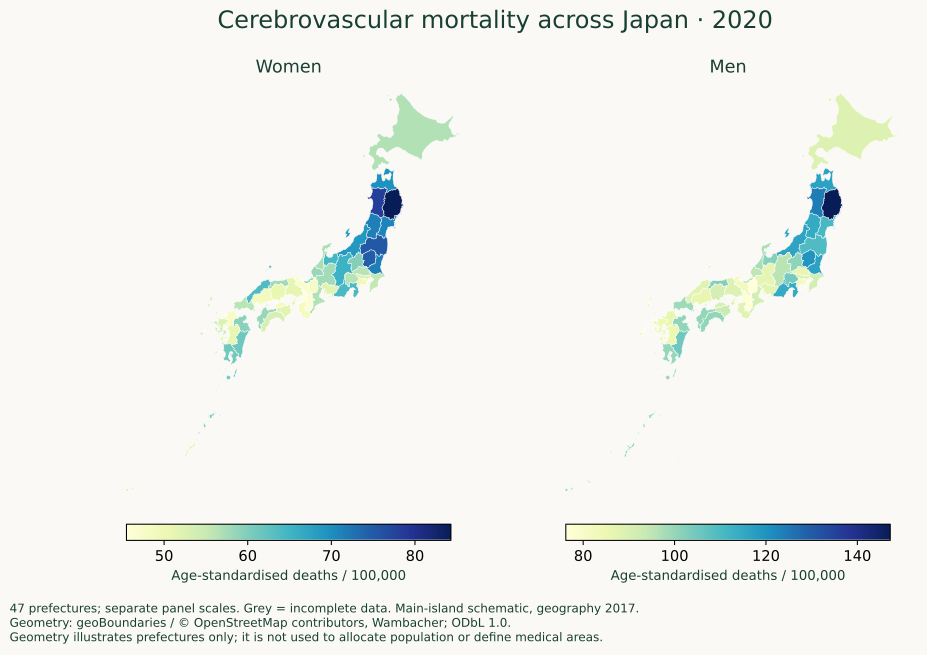
We connect public mortality, population, workforce and patient-flow data. The clearest clinical pattern is cerebrovascular: prefectures with a greater population share in rural categories have higher age-standardised cerebrovascular mortality. The pattern appears in both women and men. It does not extend uniformly to every cardiovascular cause.
These measures answer different questions and are not combined into a single access-gap score. Mortality is an outcome; older population per cardiologist is demographic context; patient flows describe how the care network operates.
A clinical signal, demographic pressure and a regional network.
1. Cerebrovascular mortality has a rural gradient in both sexes
Across 47 prefectures, the most-rural and least-rural thirds each contain 16 prefectures. The unweighted mean female age-standardised cerebrovascular death rate is 62.79 versus 51.95 per 100,000: 20.9% higher. For men it is 103.16 versus 89.19: 15.7% higher. For cerebral infarction, the corresponding contrasts are 27.6% in women and 20.8% in men.
These are comparisons of mean prefectural rates, not pooled population rates. They support investigating territorial disparities in cerebrovascular health; they do not establish a female-specific rural penalty or identify its cause.
2. The pattern depends on the disease
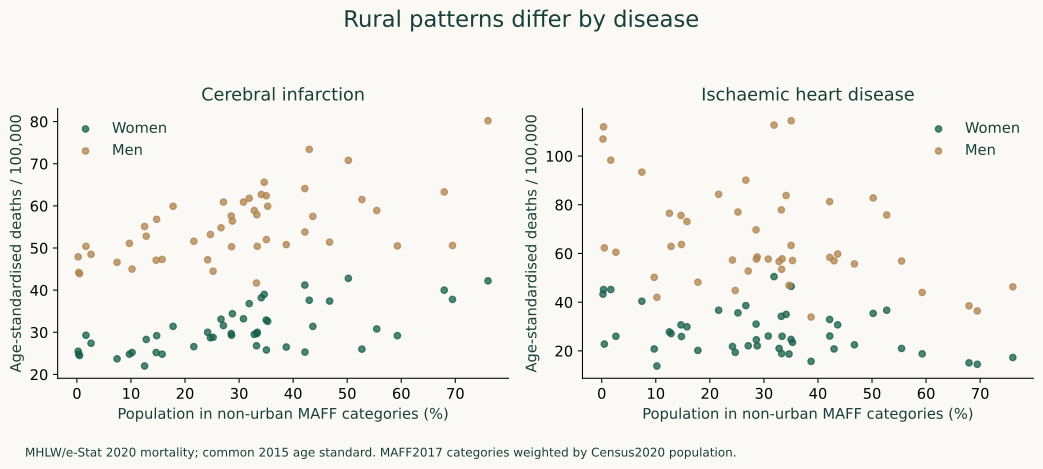
Among women, the more-rural third has a 15.8% lower mean age-standardised ischaemic heart-disease mortality rate. Broad cardiac mortality is almost unchanged between the two rurality groups. This matters: a single cardiovascular score would conceal clinically different geographies.
3. Ageing changes the population supported by specialist resources
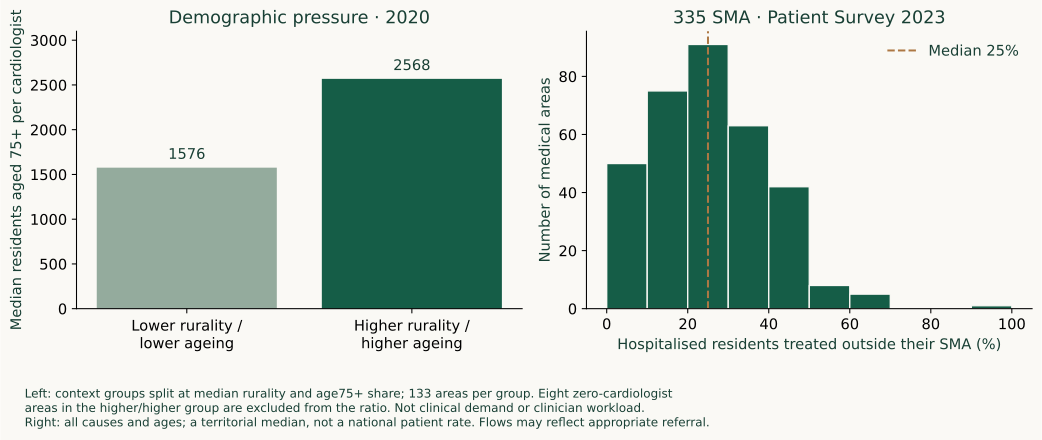
Among 335 secondary medical areas (SMAs),334 have complete age context. Splitting rural population share and the proportion aged 75+ at their respective medians creates 133 higher/higher and 133 lower/lower areas. Among areas with a nonzero cardiologist count, the median is 2,568 residents aged 75+ per cardiologist in the higher/higher group versus 1,576 in the lower/lower group: about 63% higher.
Eight areas in the higher/higher group have zero cardiologists in the underlying 2020 main-specialty table. They are reported separately and excluded from the ratio, rather than assigned an infinite or arbitrary value. Counts describe shared resources for women and men, not cardiologist sex or effective workload.
4. Patient movement is part of the care model
The 2023 Patient Survey records a median inpatient outflow of 25.0% across 335 SMAs. This is the median of territorial percentages, not the share of all Japanese inpatients. Crossing an SMA boundary can reflect appropriate specialist referral, a nearby hospital across the boundary, or limited local capacity. The table alone does not distinguish them.
Build the connection between local care and regional expertise.
The opportunity is to make referral networks easier to use while preserving specialist concentration where clinically appropriate. Regional services could evaluate three complementary pathways:
- After discharge: shared follow-up between reference hospitals and local clinicians, with clear responsibility for medication review, rehabilitation referral and escalation.
- Closer to home: rehabilitation partnerships, outreach and transport support selected according to actual services, travel time and patient circumstances.
- Supported remote contact: assisted consultations for suitable follow-up needs, alongside accessible in-person options. Acute stroke assessment and inpatient treatment are not substitutes for teleconsultation.
A useful pilot would measure missed follow-up, time to rehabilitation, completed referrals, patient travel burden and readmission, separately by sex and age. These are proposed evaluation outcomes, not benefits estimated by this analysis.
Several sources. Explicit territorial levels.
This is an ecological, exploratory public-data research brief. Mortality comparisons use 2020 official directly age-standardised rates for Japanese residents, with the same 2015 standard for both sexes. The rural measure is the 2020 Japanese population share in MAFF 2017 municipal categories other than the urban category. Prefectures are ranked once on that measure; the extreme thirds contain 16 each, with 15 in the middle.
Demographic pressure is analysed within the historical 2020 SMA context: age 75+ share median 17.08% and rural-share median 35.30%. The ratio is residents aged 75+ divided by main-specialty cardiologists, summarised by the median across eligible areas. It is not an estimate of cardiovascular need, full-time-equivalent supply or workload.
Patient Survey flows use their own 335 SMA geography and exclude unknown origins/destinations in the published percentages. Rounded counts and percentages were checked for consistency in all 335 areas. Matching SMA codes do not prove unchanged boundaries: flow data are therefore shown as a separate national distribution, not joined into a local mortality-capacity ranking.
Source URLs, dates, hashes, dictionaries and derived data are available below. Fourteen rural mortality contrasts are independently recalculated in the supplementary verification. All associations are descriptive; this brief does not report spatially adjusted effect estimates or p-values.
What these data can—and cannot—tell us.
Mortality 2020 includes the first pandemic year. Temporal stability, cause-of-death certification, clinical risk factors and spatial dependence remain unresolved. Mean prefectural comparisons do not estimate individual risk or an intervention effect. Age-standardised all-age mortality must not be presented as an outcome measured specifically in people aged 75+.
Workforce and population context are from 2020, patient flows from 2023. Resources may have changed. Prefectural results can hide differences within a prefecture; MAFF categories are a rural context proxy, not travel time. Outflow is not inherently harmful and is not a cardiovascular, sex-specific or older-patient flow estimate.
No female-cardiologist list is included. We cannot evaluate clinician gender, untreated need, eligibility for procedures or the proportion of travel that could safely be avoided. These limitations define a descriptive scope; they do not remove the value of the clinical pattern.
Bring care closer without losing regional expertise.
The strongest message is disease-specific: more-rural prefectures have higher cerebrovascular mortality in women and men, while ischaemic heart disease follows a different pattern. Alongside that clinical signal, ageing medical areas support more older residents per recorded cardiologist, and inpatient movement between medical areas is common.
The practical response to investigate is a better-connected network: strong reference centres, accessible local follow-up, rehabilitation and support for patients navigating the journey between them. The next step is to evaluate those pathways with local partners, rather than treat every outward referral as a failure.
Sources and attribution.
- MHLW Vital Statistics through e-Stat: 2020 prefectural mortality, standard population model 2015; exact cause-table URLs and hashes in the download.
- Statistics Bureau, 2020 Population Census: Japanese population by age and sex; distinct total-population living-arrangement tables are not used as denominators here.
- MAFF agricultural regional typology: 2017 municipal categories, population-weighted into territories.
- MHLW Survey of Physicians, Dentists and Pharmacists: 2020 main-specialty cardiologists; not full-time equivalents.
- MHLW Patient Survey 2023, SMA table N 3: inpatient inflow/outflow; N 1 checks rounding. Flows are not cardiovascular-specific.
- Maps: schematic 2017 prefecture geometry via geoBoundaries, © OpenStreetMap contributors / Wambacher, ODbL 1.0. Geometry is used for illustration only. Panel scales differ; colours are not comparable between panels.
Explore the evidence.
The Smart Mole Institute. Ageing beyond the city. Connecting cardiovascular care in Japan. Japan research brief JP 001. Version 1.0. 19 October 2026. Ecological descriptive research; not peer reviewed.
Machine-readable analytical record
The following appendices reproduce existing result, method, dictionary and quality records without recalculation. Large map datasets and ZIP supplements are listed in the provenance table and remain in the evidence package. Field names and original language are retained to avoid changing analytical definitions.
Availability, provenance and reproducibility limits
Figures are embedded in this HTML so they remain available after download. Links to source data and legacy supplements use the public website; the evidence ZIP preserves the available local supplements.
These materials document the analyses already carried out; this editorial conversion does not certify that an independent researcher has reproduced every result. Where the original package does not contain executable analysis code or all source inputs, that limitation remains. No missing methods, software versions or validation results have been invented.
| Preserved file | Bytes | SHA-256 |
|---|---|---|
| JP001-article.html | 659,898 | faa09cecbf3dda996f2c8509bc87cb8bc67f895c839a239fa2dc37334bed3e3b |
| JP001-citation.txt | 201 | 7bbdb5d56ac62c16501b010534d559c07882ee2f1558267500738ca4b67a475e |
| JP001-evidence.zip | 62,242 | f2a74f803ad58b1448f306ee7f48778d79dc20afa2147f935f3ddf786cc24b8f |
Citation for this technical edition
The Smart Mole Institute. Rural context, age-standardised cerebrovascular mortality, ageing and care networks in Japan. JP001. Technical report version 1.1, editorial restructuring 2026-10-20. Original publication 2026-10-19. Underlying analyses unchanged; exploratory; not peer reviewed.
Original article citation: The Smart Mole Institute. Ageing beyond the city. Connecting cardiovascular care in Japan. Japan research brief JP 001. Version 1.0. 19 October 2026. Ecological descriptive research; not peer reviewed.